



Infertility Treatment in Gurgaon:
What's Really Going On
and What Helps
How Many People Does This Actually Affect?
More than you’d guess from how quiet people stay about it. Census data from decades back put the number at around 4 to 6 percent of the population, but once primary and secondary infertility are counted together, the figure climbs to close to 17.9 million people across India. The WHO puts the rate of primary infertility in India somewhere between 3.9 and 16.8 percent, depending on which region you’re looking at.
So What is Infertility, Exactly?
Primary infertility is when a couple has never conceived, despite trying for a year or more. This tends to sit heavier emotionally. There’s no earlier pregnancy to point back to, nothing to prove the body already knows how to do this.
Secondary infertility is different. A couple already has a child, maybe two, and then it just… stops working. This one catches people off guard more than you’d expect. It worked before, so why not now? The honest answer: a lot shifts between pregnancies. Age. Weight. Hormones. Sometimes scar tissue left behind from an earlier delivery.
So What is Infertility, Exactly?
When the Cause is on the Male Side
A handful of things come up again and again:
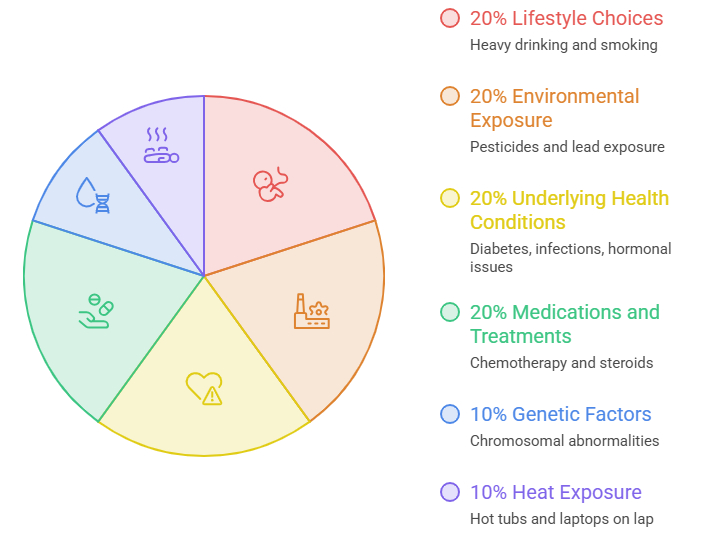
- Regular heavy drinking, which lowers sperm count and quality both
- Smoking, which hits count, movement, and shape
- Long-term exposure to pesticides or lead
- Underlying issues like diabetes, infections, or hormone imbalances
- Certain medications, chemotherapy drugs and some steroids included
- Genetic or chromosomal factors, in a smaller number of men
- Repeated heat exposure. Hot tubs are the classic example, though a laptop sitting on the lap for hours does something similar
Treatment here usually isn’t dramatic. Better diet, more movement, working toward a healthier weight, cutting back on drinking, quitting cigarettes. If there’s a real medical or genetic cause underneath, a doctor addresses that directly. None of it sounds exciting on paper. It’s still where most real progress starts.
When the Cause is on the Female Side
Some of the more common causes:
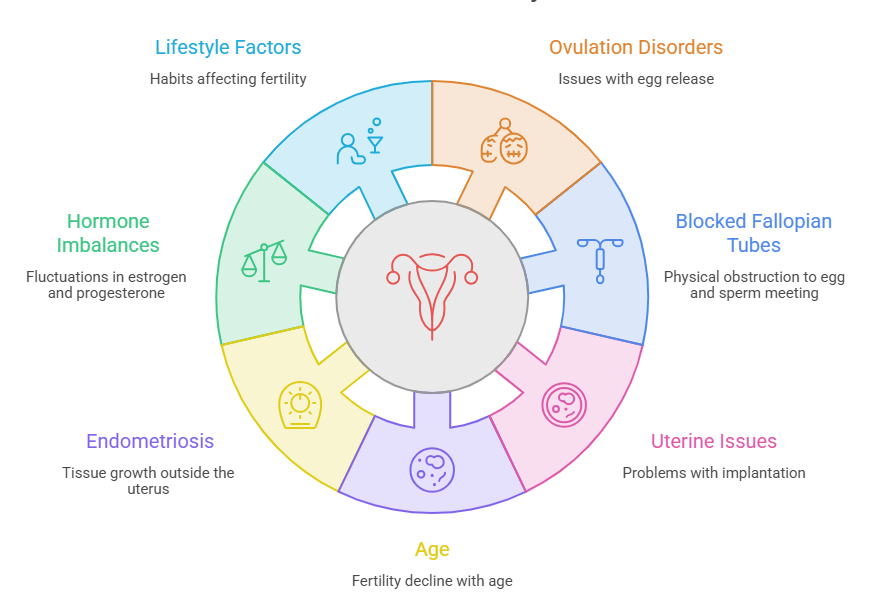
- Ovulation disorders, PCOS being the one most people have heard of, though hypothalamic issues fall here too
- Blocked fallopian tubes, which stop egg and sperm from ever meeting
- Uterine issues like fibroids, polyps, or a septum, any of which can get in the way of implantation
- Endometriosis, where tissue similar to the uterine lining grows somewhere it shouldn’t
- Age. Fertility declines gradually, then more sharply after 35
- Hormone imbalances involving estrogen or progesterone
- Lifestyle factors: smoking, heavy drinking, or big shifts in body weight in either direction
Treatment depends heavily on which of these is actually going on. A few common paths:
Medication is usually the first step when ovulation is the issue. Drugs like clomiphene citrate or letrozole are the standard starting point.
When there's a structural problem, surgery often comes next. That might mean hysteroscopic surgery to clear fibroids or polyps, laparoscopic surgery for endometriosis or blocked tubes, or removing an ovarian cyst that's in the way.
IUI places sperm directly into the uterus around the time of ovulation, giving it a better shot at reaching the egg.
Beyond IVF, other options exist too, egg donation and embryo transfer among them, for cases that call for it.
IVF involves collecting eggs and fertilizing them in a lab, then placing the resulting embryo back into the uterus. Donor eggs or sperm can be used where needed.
And then there are the everyday changes. Diet, exercise, getting to a healthier weight. Unglamorous, but genuinely useful for some women.
- If You're in the Middle of This Right Now
Worth saying plainly: the emotional side of infertility is often harder than the physical side. The waiting. The relatives who ask “any good news?” at every function without fail. The disappointment that resets every month, sometimes for years. None of that means you’re unlucky in some permanent sense, or that something is broken about you. It means you’re dealing with something medical. And medical problems generally have medical paths forward.
The first real step is getting both partners properly checked, instead of guessing where the issue might be. From there, treatment can actually be aimed at the real cause, rather than tried at random.
- Dr Amita Shah | Precision | Compassion | Care
Advanced Robotic & LaparoscopicGynecological Surgeon in Gurugram
Dr Amita Shah is one of the top Gyneacologists & is one of the best robotic laparoscopic surgeons in India for taking care of women, from adolescence to menopause to the elderly stage.
A surgeon combining decades of experience with robotic precision.
- Senior Gynecologist with 30 Years of Expertise
- Personalized & Compassionate Care
- 700+ 5-Star Reviews on Google

Frequently Asked Questions
How long should we try before seeing a fertility specialist?
A year of regular, unprotected sex without a pregnancy is the usual marker. If the woman is past 35, most doctors suggest coming in sooner, around the six-month mark, since age narrows that window a bit faster.
Is infertility usually the woman's problem?
Not really. Male factors show up in close to half of all cases, sometimes alongside a female factor too. Testing only one partner often means missing the actual cause.
Can lifestyle changes alone fix infertility?
For some couples, yes, particularly when weight, smoking, or drinking are the main drivers. For others, lifestyle changes help alongside medical treatment but aren’t enough by themselves.
Does laparoscopic surgery actually help with infertility?
Often, yes, especially when the cause is structural: fibroids, cysts, blocked tubes, or endometriosis. Clearing these out frequently restores a woman’s chances of conceiving on her own.
What's the real difference between IUI and IVF?
IUI places sperm directly into the uterus and tends to work for milder issues. IVF fertilizes the egg outside the body entirely and is used for more complicated cases, or when IUI hasn’t worked after a few tries.